
How to Run a Group Therapy Session: Outline, Stages & Free Template
A minute-by-minute session outline, the five stages every group moves through, and how to handle monopolizers.


What You'll Learn
- How to structure effective 60- and 90-minute group therapy sessions from check-in through cooldown
- How to screen prospective members and choose an appropriate group size, format, and session length
- How to recognize the five stages of group development and adjust your facilitation as the group evolves
- How to build an eight-week curriculum that progresses from safety and skill development to application and closure
- How to establish ground rules and manage common challenges such as monopolizing, conflict, silence, and inconsistent attendance
- How to write observable treatment goals and document each member’s individual response to the group session
Having a plan for a therapy group is one thing. Standing in front of eight people on a Tuesday evening and making the next 60 minutes worth their time is another. The gap between the two is where most new group facilitators struggle — and it closes faster than you’d think, because running a good group is mostly a matter of structure, preparation, and knowing what’s coming.
This guide walks through the whole arc of how to facilitate a group therapy session: who belongs in the group, how long the session should run, a minute-by-minute outline you can reuse every week, the five stages every group moves through, and what to do when one member starts taking up all the air.
Quick answer: how to run a group therapy session in 6 steps
The basic pattern of a counseling session — individual or group — is warm-up, working phase, cooldown. In group therapy, that three-part group therapy structure sits inside a stable container of ground rules, consistent membership, and a fixed start and end time. The structure is deliberately repetitive. Predictability is what makes members feel safe enough to take emotional risks.
The six steps of running a session:
Screen and prepare
Screen and prepare each member before the group starts, in an individual meeting.
Open with a warm-up
Open with a warm-up — a check-in or brief grounding exercise, 5–10 minutes.
State the focus
State the session’s focus in one sentence so nobody has to guess what the hour is for.
Run the working phase
Run the working phase — processing, skill-building, or content delivery. This is the bulk of the time.
Cool down
Cool down — lower the emotional temperature and help members re-enter their day, 5–10 minutes.
Document the session
Document the session while it’s fresh, capturing both the group intervention and each member’s individual response.

Run Your Next Therapy Group With a Clearer Plan
Download the Group Therapy Facilitator Toolkit for 15 practical, ready-to-use resources that support the entire group process—from screening prospective members and planning sessions to managing group dynamics and documenting each participant’s response.
- Group appropriateness decision tree and pre-group screening guide
- Fillable 60- and 90-minute session outlines
- Eight-week curriculum planner and measurable goals bank
- Quick references for group development, conflict, and difficult dynamics
- Client handouts, feedback forms, and a group therapy note checklist
Types of group therapy sessions
“Group therapy” covers several formats that ask very different things of the facilitator. Knowing which one you’re running tells you how much structure to bring.
Psychoeducational groups
Psychoeducational groups teach content — what a diagnosis is, how a medication works, what maintains a symptom. Highly structured, easiest to lead as a new facilitator.
Skills groups
Skills groups teach and practice specific techniques (DBT skills training is the best-known example). Structured, with in-session rehearsal and between-session homework.
Process groups
Process groups work on the live interaction between members rather than outside content. Least structured, deepest relational change, most demanding to lead.
Support groups
Support groups center shared experience and mutual aid around a common condition or loss. Often facilitated lightly; sometimes peer-led.
Experiential and activity groups
Experiential and activity groups use art, movement, music, or a shared task as the medium, then process what came up.
Closed vs. open groups
A closed group starts and ends together with fixed membership and a curriculum. An open, rolling-admission group takes new members continuously — which means it cycles back through the early stages every time someone joins.
How to start a therapy group: screening, size, and session length
Most of what determines whether a group works is decided before anyone sits down — which is why how to start a therapy group is really a question about these three choices, not about session one.
Screen every member individually
Not every client is a fit for every group. A pre-group interview lets you assess whether a prospective member can tolerate the format, whether their goals align with the group’s purpose, and whether they’re likely to help or hinder the others. It also lets you do the preparation half of the conversation: explaining what group involves, what’s expected of them, and what confidentiality does and doesn’t cover.
The balance you’re aiming for is similarity of purpose with diversity of experience. A grief group needs members who share a comparable sense of loss — but if every member has lost a spouse in the same way, the group loses the varied perspectives that make it more useful than individual therapy.
Screen for a few specific risks: active psychosis or acute intoxication that would make participation unsafe, an inability to maintain confidentiality, existing outside relationships with other members that would distort group dynamics, and a crisis level that genuinely needs a higher level of care first.
How many people should be in a therapy group?
Groups function anywhere from three to fifteen members, but most practitioners find seven or eight to be the sweet spot. Below five, a single absence can hollow out the session. Above ten, quieter members reliably disappear and the facilitator spends more time managing airtime than doing therapy.
Because attendance is never perfect, recruit above your target. If you want eight in the room, enroll ten to twelve.
How long should a group therapy session be?
Sixty to ninety minutes is standard for outpatient groups. Sixty minutes works for psychoeducational and skills groups where you’re delivering structured content. Ninety is better for process groups, where members need time to get past the surface — the real material in a process group often doesn’t surface until minute 40.
Intensive outpatient and partial hospitalization programs typically run multiple 60- to 90-minute groups per day. Whatever you choose, hold it. Ending late teaches members that the boundary is negotiable, and the boundary is part of the treatment.
A group therapy session outline you can reuse
The single most useful thing you can build for yourself is a session outline you run every week. Group therapy session plans change week to week; the schedule inside the hour shouldn’t. Here’s a 60-minute structure:
| Time | Segment | What happens |
|---|---|---|
| 0:00–0:05 | Arrival & settling | Greet members by name. Note who’s missing. Restate the ground rules briefly in the first few sessions and any time a new member joins. |
| 0:05–0:15 | Check-in / warm-up | A round where each member gives a brief update — a word for their mood, one thing from the week, or progress on last session’s commitment. Keep it timed. |
| 0:15–0:18 | Frame the session | Name the focus in one sentence: “Tonight we’re working on what to do when the urge hits and you’re alone.” |
| 0:18–0:45 | Working phase | The therapy itself — processing, a skills teach-and-practice, an experiential exercise, or member-led content. Link individual shares to universal themes so the whole group benefits from one person’s work. |
| 0:45–0:55 | Consolidation | What’s the takeaway? A go-round on one thing each member is carrying out of the room, plus any between-session commitment. |
| 0:55–1:00 | Cooldown & close | Lower the emotional temperature. A grounding breath, a brief closing ritual, a reminder of the next meeting time and crisis resources. |
And the 90-minute version, which mostly buys you a longer working phase:
| Time | Segment |
|---|---|
| 0:00–0:10 | Arrival, settling, ground rules |
| 0:10–0:25 | Check-in round |
| 0:25–0:30 | Frame the session |
| 0:30–1:10 | Working phase (often two movements: content, then processing) |
| 1:10–1:22 | Consolidation and commitments |
| 1:22–1:30 | Cooldown and close |

Two things about the warm-up and cooldown that facilitators underestimate. The warm-up isn’t filler — it’s the ritual that tells members’ nervous systems they’ve arrived somewhere safe, and skipping it produces a flat, guarded session. And the cooldown is a clinical safeguard: sending someone back into their car and their commute while still highly activated is a real risk. It isn’t always avoidable, but it should never be accidental.
How to build an 8-week group therapy curriculum
A closed group with a fixed end date needs an arc, not eight interchangeable sessions. A curriculum that works generally moves from safety to skills to integration:
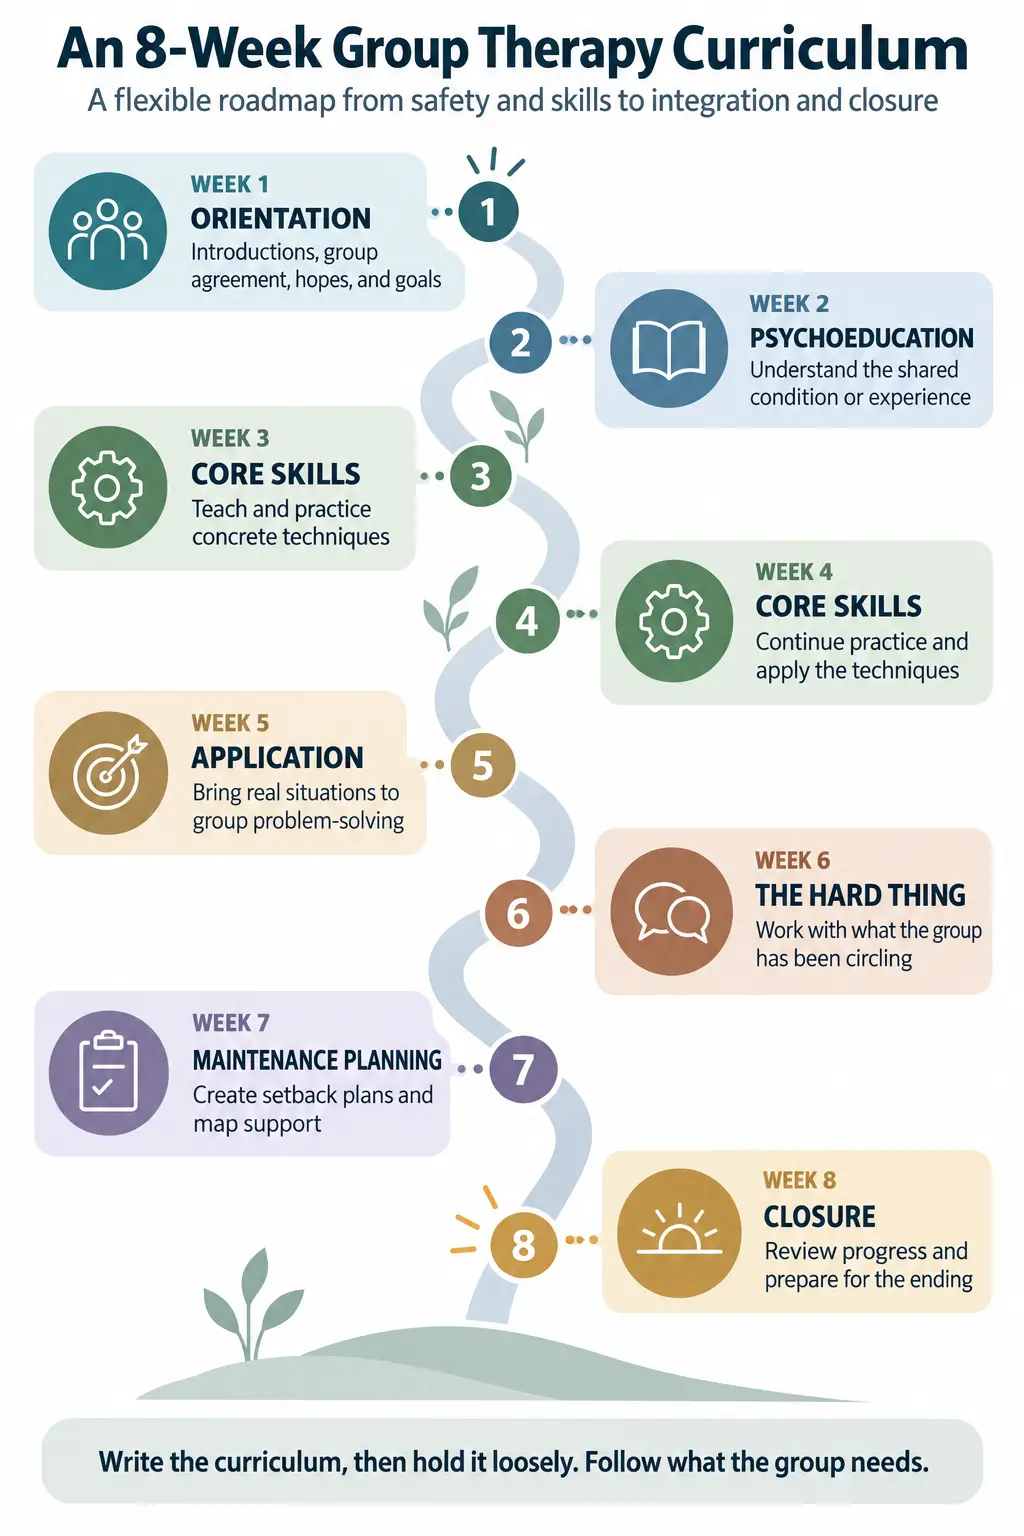
- Week 1 — Orientation. Introductions, group agreement, hopes and fears, individual goals.
- Week 2 — Psychoeducation. The shared condition or experience: what it is, how it works, what maintains it.
- Weeks 3–4 — Core skills. Two or three concrete techniques, taught and practiced in session.
- Week 5 — Application. Members bring real situations and the group problem-solves them together.
- Week 6 — The hard thing. Whatever the group has been circling: shame, relapse, conflict, grief. Save it for when trust can hold it.
- Week 7 — Maintenance planning. Relapse or setback plans, support mapping, what happens when this ends.
- Week 8 — Closure. Review actual outcomes against week-1 goals, name what worked, make room for the loss of the group itself.
Write the curriculum, then hold it loosely. If week 4 surfaces something the group needs to stay with, staying with it is better therapy than moving on because the plan said to.
How to facilitate a group therapy session
For yourself and for your members, clarify your role from the outset. What kind of facilitator are you going to be, and what kind do they need you to be?
An active, vocal, directive therapist brings very different energy to the room than one who is intentionally quiet and lets the group find its own way. Both are legitimate, and the right choice depends on the group, its members, and its goals. A skills group for newly diagnosed adolescents wants direction. A long-running process group for experienced members usually wants you to stay out of the way.
Leading a group is a chance to try on different hats. You want to be authentic — but exaggerating or dialing back particular parts of your style produces versions of you that serve different groups better. What matters most is that your members aren’t guessing. Say out loud, in session one, how you intend to work and what you’ll expect of them.
Set ground rules the group will actually hold
A handful of rules are non-negotiable and come from you: confidentiality, no contact outside group without disclosing it, no violence or threats, arriving sober. Beyond those, let the group write its own. Members who author the norms feel invested in them and enforce them on each other, which is far more powerful than enforcement from the facilitator.
Put the agreement in writing and have members sign it before the first session. It doubles as clinical documentation of informed consent.
For sample language, a client-facing agreement, and guidance on enforcing norms without turning into a hall monitor, see our full guide to group therapy ground rules.
The five stages of group therapy
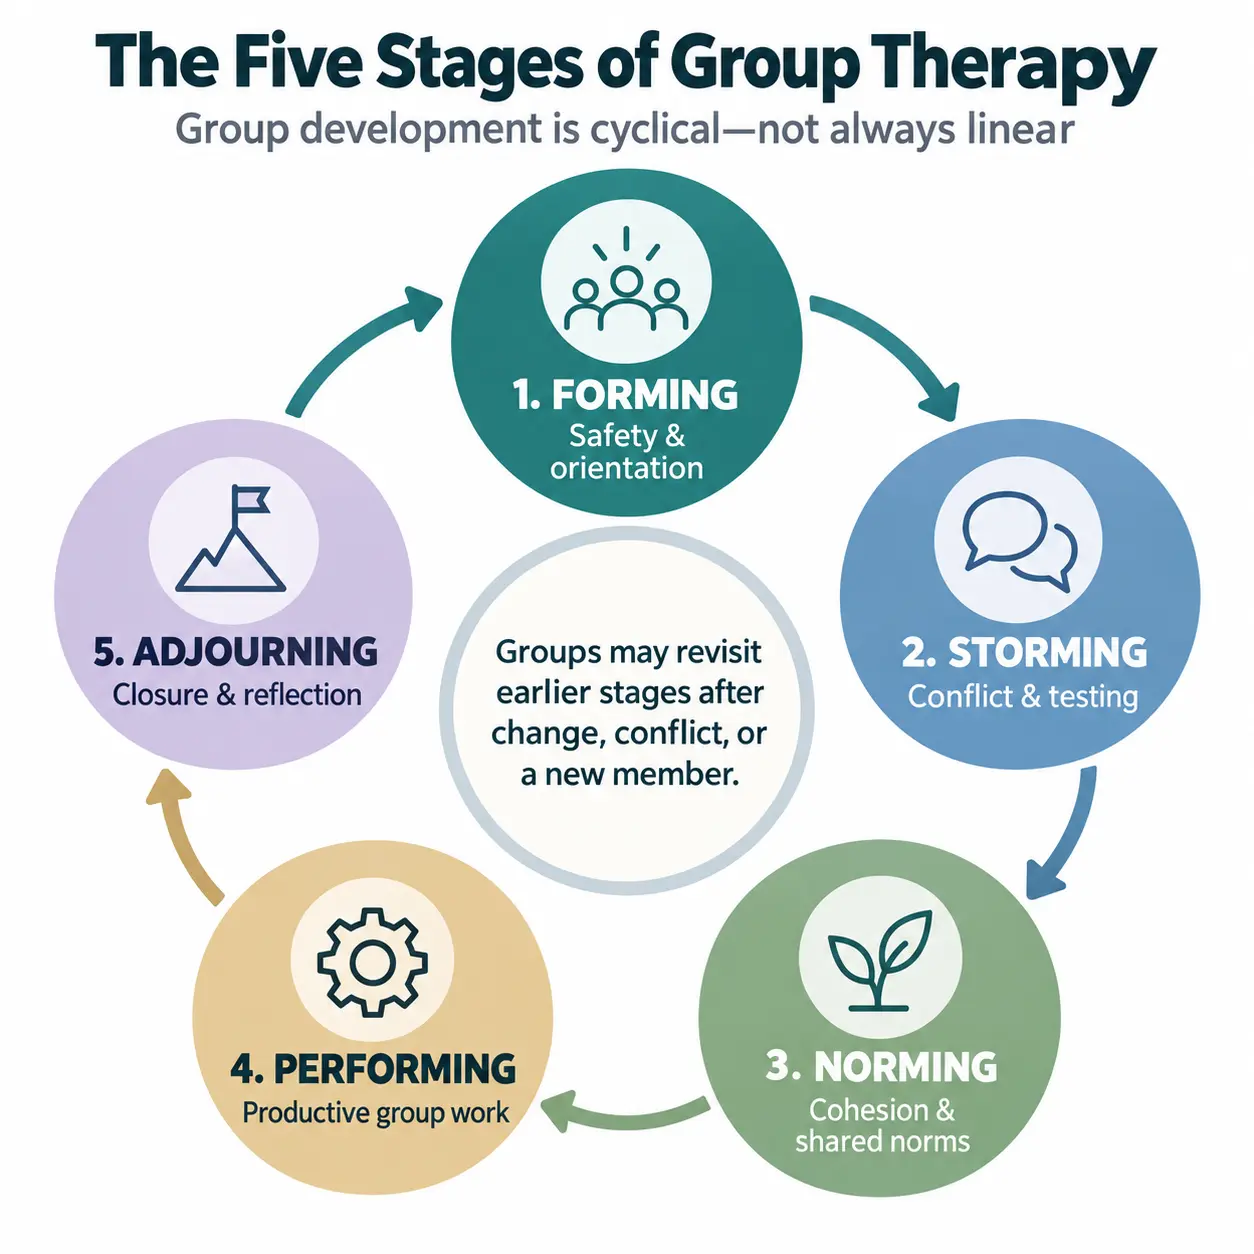
Groups develop, and the group therapy stages are predictable enough to plan around. The session that flopped in week three may have flopped because the group was exactly where it was supposed to be, doing exactly what that stage requires. Bruce Tuckman’s model of group development — forming, storming, norming, performing, adjourning — maps onto therapy groups closely enough to be genuinely useful at the whiteboard, and it lines up with what Irvin Yalom described as the movement from orientation, through conflict and dominance, into cohesion.
| Stage | What it looks like | What the facilitator does |
|---|---|---|
| 1. Forming | Polite, tentative, surface-level. Members look to you for direction and test whether this is safe. Disclosure is guarded. | Be more active than you will be later. Provide structure, model disclosure at an appropriate depth, establish norms, and name the awkwardness out loud. |
| 2. Storming | Conflict, jockeying for position, challenges to you or to the group’s purpose. Anxiety and ambiguity rise. Members may go quiet, arrive late, or drop out. | Don’t smooth it over. Conflict that gets worked through is what proves the group can survive disagreement. Stay non-defensive when the challenge is aimed at you — it usually is. |
| 3. Norming | Cohesion forms. Members start policing lateness themselves, develop shared language and in-jokes, and begin caring about each other’s outcomes. | Step back. Reinforce helpful norms by naming them. Resist the urge to fill silences the group is capable of filling. |
| 4. Performing (the working stage) | The working stage of group therapy is the productive phase. Members take real risks, give each other honest feedback, and experiment with new behavior inside the group. This is where change happens. | Mostly get out of the way. Link members to each other rather than to you, keep the here-and-now in focus, and protect the container. |
| 5. Adjourning | Endings — of the group, or of one member’s time in it. Often a regression: old symptoms resurface, members minimize the group’s importance, attendance slips. | Name the ending several sessions early. Review outcomes against original goals. Make explicit room for loss instead of letting the group dissolve quietly. |
Stages aren’t a staircase. Groups revisit storming when a new member joins, slide back toward forming after a long break, and can cycle through several stages inside a single difficult session. The value of the model isn’t prediction — it’s that it stops you from reading a hard week as a personal failure.
Process group therapy: how it works, with examples
A process group works on what’s happening in the room rather than on a topic brought in from outside. The material is the interaction itself: who interrupts whom, who goes quiet when conflict starts, what it’s like to receive praise from a stranger. Because members recreate their outside relational patterns inside the group, the group becomes a place to notice and change them in real time.
Some process-group sessions look, on the surface, like they have nothing to do with therapy. That’s the point. Five process group therapy examples:
- The jigsaw puzzle. Give the group a puzzle and 20 minutes. Who takes charge? Who withdraws? Who works alone at the edge of the table? Then spend the rest of the session on what happened. If one of your goals is communication skills, a task that teamwork either helps or hinders will surface more than an hour of discussion about communication.
- The unstructured opening. Start with “the floor is open” and nothing else. The silence, and who breaks it, is the content.
- Feedback rounds. Each member tells one other member one thing they appreciate and one thing they find difficult. Handle only in a group that has reached norming or later.
- Group decision under constraint. The group has ten minutes to agree on one thing — next week’s topic, a group name. Watch the coalition-building.
- The empty chair. One member addresses an absent person; the group reflects back what they observed. Powerful, and demanding — this one needs a group that has earned it.
Use process sessions deliberately rather than constantly. They can pull a topic-focused group off course. The fix is always the same: process the process. Spend real time afterward — or at the start of the next session — connecting what happened during the exercise back to why the group exists.
How to plan engaging group therapy content
The simplest lever on group success is whether the group is worth attending. Make it worth coming to and members attend consistently; attend consistently and they improve.
The old idiom “don’t work harder than your clients” doesn’t hold in group work, at least not early. A facilitator has to work hard on the planning, preparation, and execution of the first few sessions, because those sessions set the tone for everything after.
Four questions to run any planned content through:
- What do they already know? Repetitive or basic material disengages people fast. A client six months into recovery does not need the definition of a trigger.
- What do they want to know? Fascinating, beautifully delivered content falls flat if the group doesn’t care about it. Ask them. Then actually use the answers.
- What are their individual goals? One member wants to talk at length; another wants only to receive information. Those two will not experience the same session the same way, and planning has to account for both.
- What are you actually good at? Don’t lecture for 60 minutes if presenting isn’t your strength, and don’t open up open-ended trauma processing if managing intense affect in a room of eight is still hard for you. Lean on your strengths, experiment at the edges, and let the group get stronger over time.
For ready-made material, see our collections of group therapy activities for substance use, group therapy activities for teens, and life skills group activities for adults.
How to write measurable group therapy goals
Groups need two layers of goals: one for the group and one for each member. The group-level goal is the reason the group exists. The individual goals are what make your documentation defensible and what let you demonstrate that a particular client benefited from a particular session.
The move that makes goals documentable is turning an aspiration into an observable behavior with a frequency and a timeframe. Compare:
- Aspirational: “Client will improve social skills.”
- Documentable: “Client will initiate conversation with at least one group member in 3 of 4 consecutive sessions.”
- Aspirational: “Client will manage anger better.”
- Documentable: “Client will identify two personal anger triggers and demonstrate one de-escalation skill in session by week 6.”
Write them this way at intake and each session’s note practically fills itself, because you already know what you’re looking for.
Managing difficult group dynamics
Adding positives to the group experience is essential, but sometimes the only way to truly optimize a group is by targeting what’s undermining it. Five patterns account for most of the trouble.

- The member who monopolizes. One person taking more than their share of the time frustrates everyone else and drives disengagement. Use structured go-rounds to distribute airtime by design rather than by intervention, and when you do intervene, be direct and warm: “I want to hold that for a moment and hear from a few others, and then come back to you.”
- The member who distracts. Chronic lateness, frequent absence, stepping out mid-session, side conversations. Each one breaks the focus and flow. Address the behavior privately first; if it persists, bring it to the group as a group issue, because by then it is one.
- The member who instigates. Aggressive communication styles can spark conflict as a way to deflect from their own material or to enact some rough justice in the group. Name the pattern without shaming the person, and treat the conflict as workable content rather than an emergency. Our guide to conflict resolution in group therapy goes deeper on this.
- The member who never speaks. Silence isn’t automatically a problem — some members do real work while listening. It becomes a problem when it’s avoidance. Lower the cost of entry: ask for a one-word contribution, a written response, or agreement with someone else’s point rather than a monologue.
- The chronically absent member. Erratic attendance destabilizes the group more than departure does, because the group can never settle into who it is. Have an attendance policy, state it in session one, and enforce it. A clear policy is kinder than a vague one.
How you resolve any of these depends on the group and on you. Experienced facilitators tend to balance handling the issue individually with making it a named group topic — and letting every member take some role in reducing the problem is often what unifies the group.
Solicit feedback with a group therapy evaluation form
You will not reliably know how the group is landing unless you ask in a way that’s safe to answer honestly. A short evaluation form lets members say what’s working and what isn’t. Ideally they’d bring that directly to the group — but many will only say the real thing anonymously, and the anonymous version is still worth having.
Keep it to four or five questions, run it at the midpoint and at the end, and then visibly change something based on the answers. Collecting feedback and ignoring it is worse than not asking.
Documenting group therapy sessions
Group documentation has a requirement individual notes don’t: each note has to capture both the group-level intervention and the individual client’s distinct response to it. Identical notes across eight members is one of the most common findings in a behavioral health audit, and it’s the fastest way to have group sessions recouped.
A defensible group note records the group’s topic and intervention, that specific client’s participation and affect, progress toward their individual treatment plan goals, and the clinical plan going forward — without naming other members.
ICANotes was built for this. Group session documentation pulls the shared content once and then prompts for each member’s individual response, so eight notes take a fraction of the time and none of them look alike. Session content, attendance, and progress toward goals stay linked to each client’s chart, which means the record supports the billing rather than contradicting it.
For structure and examples, see our group therapy note template and examples. If you’re weighing platforms, we also compare the best EHRs for group therapy practices.
Final thoughts
Group therapy sessions become almost self-sufficient as time and trust build. At the beginning, though, facilitators have to stay on their toes to manage what presents. Group work pushes the boundaries of creativity and the artful use of clinical skill — and when it’s done well, the benefits far outweigh the risks.
Running a group well comes down to preparation, adaptability, and engagement. Screen carefully, establish a clear structure, plan content your members actually want, expect the stages, and address risks early. The effort you put into the first four sessions sets the tone for everything that follows.
Key takeaways
- Screen and prepare every member individually before session one.
- Run a consistent warm-up, working phase, and cooldown every week.
- Seven or eight members and 60–90 minutes are the outpatient sweet spots.
- Expect the five stages — a hard week may just be the stage doing its job.
- Document each member’s distinct response, never identical notes.
Document every group session without eight identical notes
ICANotes pulls the shared group content once, then prompts for each member’s individual response — so your record supports the billing instead of contradicting it.
- Group notes that capture each member’s distinct response
- Shared intervention entered once, individualized per client
- Attendance and goal progress linked to each chart
- Audit-ready notes that avoid recouped sessions
See how ICANotes can reduce time spent on group therapy documentation. Start your free 30-day trial, no credit card required.
Start Your Free 30-Day Trial
Explore ICANotes and see how it can simplify your clinical workflow. No credit card required.
Frequently Asked Questions About Facilitating a Group Therapy Session
How do you structure a group therapy session?
How long should a group therapy session be?
How many people should be in a therapy group?
What are the five stages of group therapy?
What is a process group in therapy?
What is the difference between a process group and a psychoeducational group?
How do you handle a group member who talks too much?
Do you need a ground rules agreement for group therapy?
How do you document a group therapy session?
References
- Substance Abuse and Mental Health Services Administration. Substance Abuse Treatment: Group Therapy (TIP 41).
- American Group Psychotherapy Association. What is Group Psychotherapy?
- Australian Institute of Professional Counsellors (2011). Skills and Role of the Group Therapist.
- Novotney, A. (2019). Keys to great group therapy. Monitor on Psychology, American Psychological Association.
- Tuckman, B. W. (1965). Developmental sequence in small groups. Psychological Bulletin, 63(6), 384–399.
- Yalom, I. D., & Leszcz, M. The Theory and Practice of Group Psychotherapy.
- Group Therapy. StatPearls, NCBI Bookshelf.
Eric Patterson
Eric Patterson is a professional counselor who has been working for over a decade to help children, adolescents, and adults in western Pennsylvania reach their goals and improve their well-being. Along the way, Eric worked as a collaborating investigator for the field trials of the DSM-5 and completed an agreement to provide mental health treatment to underserved communities with the National Health Service Corp.





